Patello-femoral Syndrome

The Q-angle (quadricep angle) is a measurement used by many health care practitioners to assess patello-femoral alignment. It is often mentioned in running magazines and on different websites because of its apparent ability to identify those persons at risk of certain knee injuries. Some of these knee injuries include patellofemoral syndrome, patellofemoral maltracking, chondromalacia patella, patellar tendinosis, patellar tendinitis, osteoarthritis and “runners knee”. But is it a valid measurement tool?
Patellofemoral Syndrome – Diagnosis
The basic premise of the Q-Angle is that a higher angle (such as what might be expected in people with a wider pelvis) would affect the way that the patella (knee-cap) lines up with the lower limb. Some practitioners use it to identify those patients at risk of patellofemoral syndrome. According to the scientific literature though, the Q-Angle is a measurement which over-simplifies knee biomechanics. It only examines a person in one plane of reference (like a two-dimensional object) and does not take into account the complex forces that occur during running, walking and jumping. Numerous publications in very reputable journals have scrutinized its ability to accurately identify those people at risk of knee pain and patellofemoral syndrome.

Patellofemoral Syndrome Risk Factors
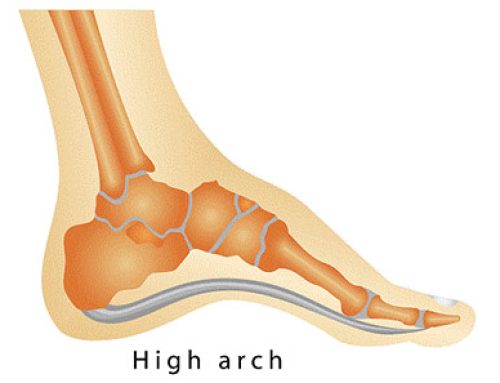
Traditionally, the risk factors for patellofemoral pain have been pinned on different aspects of the knee itself. These include malalignment of the patellofemoral joint, an imbalance in the muscles around the joint, weakness in the quadriceps, and abnormalities in the bone. Interestingly, the research has never quite agreed on whether fallen arches play any meaningful role, which is a good reminder that the picture is more complicated than a single cause. Patellofemoral pain is also one of the most common complaints among distance runners, where injury rates are estimated to land somewhere in the range of 37 to 56%.
Patellofemoral Pain and Running Impact
There is one more factor worth knowing about, especially if you are a runner. A 2008 study published in the British Journal of Sports Medicine found that patellofemoral pain can be related to impact, not just alignment. Specifically, the runners who went on to develop patellofemoral pain tended to land with higher impact on the outside of the heel at footstrike, and through the second and third toes during push-off. In other words, how hard and where you land matters, not only how your knee is built. We do not recommend changing your running technique without guidance from a qualified professional, but if you know you are a heavy lander, lightening your step is one thing worth looking at.
Patellofemoral Syndrome – Treatment
The treatment for patellofemoral syndrome varies, depending on the specific nuances of each individual case. At our physiotherapy and chiropractic clinic in Burlington, we try to use good science to guide our decisions and our advice. Commonly, the treatment for patellofemoral syndrome involves soft tissue therapy and strengthening exercises, often aimed at the gluteals and the inner quadricep while releasing the tighter structures on the outside of the thigh and the iliotibial band. Obviously, the best course of action is to give our clinic a call and speak with one of our practitioners. In the meantime you may want to take a look at our services page; specifically our active release technique and our graston page. Curious about who will be helping you with your injury? Check out our practitioners page! 905.220.7858 info@burlingtonsportstherapy.com
References
Duffey MJ, Martin DF, Cannon DW et al. Etiologic factors associated with anterior knee pain in distance runners. Med Sci Sports Exerc. 2000; 32: 1825-1832.
Nguyen AD, Boling MC, Levine B, Shultz SJ. Relationships between lower extremity alignment and the quadriceps angle. Clinical Journal of Sports Medicine. 2009; 19(3): 201-206.
Thijs Y, Clercq D, Roosen P, Witvrouw E. Gait-related intrinsic risk factors for patellofemoral pain in novice recreational runners. British Journal of Sports Medicine 2008; 42: 466-471.
Thomee R, Renstrom P, Karlsson J et al. Patellofemoral pain syndrome in young women. A clinical analysis of alignment, pain parameters, common symptoms and functional activity level. Scand J Med Sci Sports. 1995; 5: 237-244.
Witvrouw E, Lysens R, Bellemans J et al. Intrinsic risk factors for the development of anterior knee pain in an athletic population. A two-year prospective study. American Journal of Sports Medicine 2000; 28: 480-489.
Disclaimer https://burlingtonsportstherapy.com/blog/disclaimer/